

TL;DR:
- A copay is a fixed fee charged for specific covered services, and most surprise bills occur when patients assume it covers more than it does.
- Understanding copays, deductibles, and coinsurance is essential because each has different rules and impacts your healthcare costs significantly.
A copay is a plan-defined flat fee for a specific covered service. It’s a billing rule set by your insurer, not a signal of care quality or a catch-all for every cost you’ll face at a provider’s office. Most surprise bills happen because patients assume their copay covers more than it actually does.
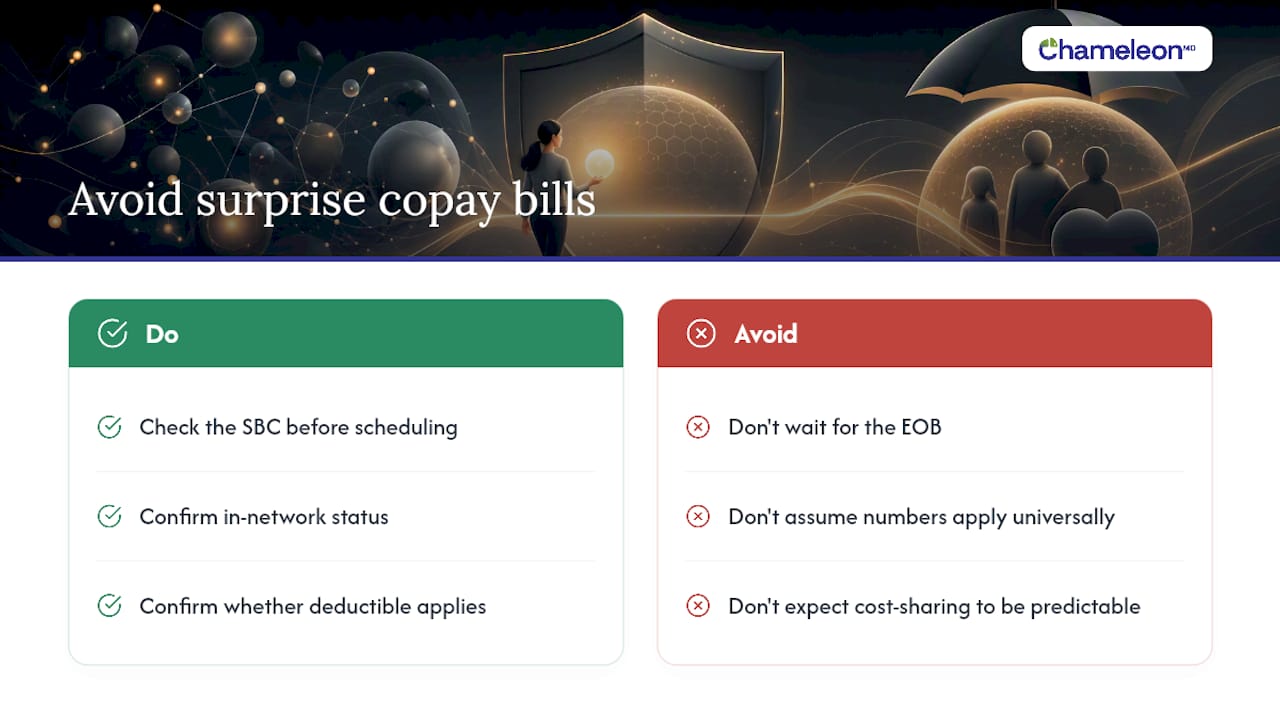
Before your next appointment, take three quick steps:
- Pull your Summary of Benefits and Coverage (SBC) and look up the specific service you need.
- Confirm your provider is in-network before you schedule, not after.
- Ask whether the service is classified as preventive, since ACA-required preventive care is covered at $0 cost-sharing when delivered in-network.
Pro Tip: Your insurance ID card lists common copay amounts on the front, but it won’t show every service tier. Always cross-check with the SBC for labs, imaging, or specialist visits, since those often use coinsurance instead of a flat copay.
Table of Contents
- What a copay is and how it usually works in U.S. health plans
- Common copay misconceptions, corrected one by one
- How copays, deductibles, and coinsurance actually differ
- Do copays count toward your deductible or out-of-pocket maximum?
- How to avoid surprise copays before your next visit
- When telehealth or direct-pay care removes the copay guessing game
- Key Takeaways
- Clear pricing, no copay math required
- Authoritative sources worth bookmarking
What a copay is and how it usually works in U.S. health plans
A copay (short for copayment) is a fixed dollar amount you pay for a covered service at the time of care, regardless of the total bill. Your insurer pays the rest, up to the plan’s allowed amount.
Plans set copay amounts through their benefit design, which typically organizes services into tiers. A primary care visit might carry a modest copay, a specialist visit a higher tier copay, and brand-name prescriptions are often more costly than generic ones. These amounts are printed on your ID card and spelled out in the SBC. The plan negotiates rates with providers and then assigns a flat fee to each service category, so the copay you pay has nothing to do with the individual doctor’s skill or the clinic’s reputation.
Here’s what that looks like in practice. You visit your primary care doctor for a sinus infection: you hand over $30 at the front desk and leave. Two weeks later, you see a cardiologist: the copay jumps to $60 because specialists sit in a higher tier. At the pharmacy, your generic antibiotic costs $10, but a brand-name allergy medication runs $45. Same plan, same day, three different flat fees because each service falls into a different benefit tier.
Common copay misconceptions, corrected one by one
The AMA Foundation notes that patients regularly misidentify which services carry a copay versus which trigger deductible-first or coinsurance pricing, and that confusion is exactly what drives unexpected bills. Here are the ten myths worth clearing up.
1. A higher copay means a better doctor
Myth: Paying $75 to see a specialist means you’re getting higher-quality care than the $25 primary care visit.
Reality: Copay tiers reflect how your insurer categorizes provider types, not clinical quality. A specialist copay is higher because the plan places specialists in a pricier tier. The dollar amount is a billing classification, full stop. UnitedHealthcare confirms that copay amounts are set by the plan’s benefit design and carry no information about provider quality.
2. Copays always count toward your deductible
Myth: Every dollar you pay as a copay chips away at your deductible.
Reality: Most plans keep copays and deductibles in separate buckets. Verywell Health explains that copays typically do not reduce your deductible, though they usually do count toward your annual maximum out-of-pocket (MOOP). You could pay dozens of office-visit copays across the year and still owe your full deductible when you need surgery.
3. A copay covers everything from that visit
Myth: You paid your $40 office-visit copay, so the whole appointment is settled.
Reality: The copay covers the visit itself. Labs drawn during that same appointment, imaging ordered on the same day, or a procedure performed in the office may each trigger separate cost-sharing, often coinsurance or deductible-first pricing rather than a flat fee. One visit, multiple line items.
4. Out-of-network copays are the same as in-network
Myth: Your plan has a copay for specialist visits, so it applies wherever you go.
Reality: Out-of-network providers are billed differently. Your plan may apply a higher copay, switch to coinsurance, or offer no coverage at all. Worse, out-of-network providers can bill you for the gap between their charge and the plan’s allowed amount, a practice called balance billing. Always confirm network status before the appointment.
5. The ER copay is your total emergency bill
Myth: You paid the $250 ER copay, so you’re done.
Reality: The ER copay typically covers the facility fee for the visit. Physician services, labs, imaging, and any procedures performed during that visit are billed separately and often use coinsurance after the deductible. A single ER visit can generate four or five separate claims.
6. Preventive care always has a copay
Myth: Every time you see a doctor, you owe a copay.
Reality: ACA-required preventive services, like annual wellness exams, recommended screenings, and certain immunizations, must be covered at $0 cost-sharing when delivered by an in-network provider. The catch: if your doctor addresses a new symptom or condition during the same visit, that portion may be billed as a separate, non-preventive service with its own copay or coinsurance.
7. HDHPs work just like regular copay plans
Myth: All health plans use copays for routine visits.
Reality: High-deductible health plans (HDHPs) often skip copays entirely for non-preventive services until you’ve met your deductible. MoneyGeek notes that HDHP enrollees typically pay the negotiated provider rate out of pocket until the deductible is satisfied. If you’re used to a $30 copay and you switch to an HDHP, that same visit might cost $150 pre-deductible.
8. Telehealth visits always carry the same copay as in-person visits
Myth: A virtual visit costs the same as walking into the office.
Reality: Telehealth copays vary widely by plan. Some plans charge the same as a primary care visit, others set a lower flat fee, and some plans have changed their telehealth cost-sharing since pandemic-era rules expired. Check the SBC specifically for “telehealth” or “virtual visit” to find the correct amount.
9. Prescription copays are the same at every pharmacy
Myth: Your $15 generic copay applies wherever you fill the prescription.
Reality: Plans use pharmacy networks, and out-of-network pharmacies may charge more or not be covered at all. Mail-order pharmacies often carry lower copays for maintenance medications. Specialty drugs may sit in a separate tier with coinsurance rather than a flat copay.
10. Comparing plans by copay alone tells you which plan is cheaper
Myth: The plan with the lowest copay is the best deal.
Reality: MetLife advises that comparing plans on copay alone is a mistake. A plan with a $10 primary care copay might carry a $4,000 deductible and 30% coinsurance, making it far more expensive for anyone who needs specialist care, labs, or hospitalization. Review the premium, deductible, coinsurance rate, and MOOP together for a real picture of value. The SBC is built precisely for this kind of side-by-side comparison.
Pro Tip: When comparing plans, search the SBC for “What You Will Pay” — that column shows copay, coinsurance, and deductible rules for each service category in one place.
How copays, deductibles, and coinsurance actually differ
Copays are fixed and predictable. Deductibles and coinsurance are variable and can scale with the cost of care. That distinction matters most when you need expensive services.
Investopedia explains that a copay is a set fee while coinsurance is a percentage of the allowed charge, and insurers use both to shape how patients use care. Here’s how the three types compare:
| Cost-sharing type | What it is | When it applies | Predictability | Common services |
|---|---|---|---|---|
| Copay | Fixed dollar amount | At point of service, often before deductible | High | Office visits, Rx, urgent care |
| Deductible | Amount you pay before insurance kicks in | Before most benefits activate | Moderate | Labs, imaging, inpatient |
| Coinsurance | Percentage of the allowed charge | After deductible is met | Low | Surgery, specialist procedures |

A quick example shows why coinsurance can hurt more than a copay. Suppose you need an MRI. Your plan has a $50 imaging copay — but only if the plan assigns one. If instead the MRI falls under 20% coinsurance after a $1,500 deductible, and the allowed amount is $1,200, you owe $240 in coinsurance alone, plus whatever remains of your deductible. The percentage-based model scales with cost in a way a flat copay never does. For a deeper look at out-of-pocket expense types, the breakdown is worth bookmarking before open enrollment.
Do copays count toward your deductible or out-of-pocket maximum?
Copays generally do not count toward your deductible, but they do count toward your annual maximum out-of-pocket (MOOP). That’s the practical budget cap for a plan year, after which your insurer covers 100% of covered services.
| Cost-sharing type | Counts toward deductible? | Counts toward MOOP? |
|---|---|---|
| Copay | No (most plans) | Yes |
| Deductible payments | Yes | Yes |
| Coinsurance | No | Yes |
Here’s why that matters in real life. Imagine you have a deductible and a maximum out-of-pocket (MOOP). You pay copays for office visits throughout the year, which count toward your MOOP but not toward your deductible. If you then need surgery, you still owe the full $1,500 deductible before coinsurance kicks in. Verywell Health confirms this is how most plans work, though you should always verify in your own SBC since plan rules vary. A plain-language guide to premiums and deductibles can help you map out the full picture before you need care.
How to avoid surprise copays before your next visit
A little preparation before the appointment saves a lot of frustration at checkout.
- Use your HSA or FSA. Copays, deductibles, and coinsurance all qualify as eligible expenses. Pre-tax dollars reduce the real cost of every payment. For more ways to reduce healthcare costs, an HSA paired with an HDHP is one of the most effective tools available.
Sample one-minute call script: “Hi, I have an appointment scheduled for [service] with [provider]. Can you confirm they’re in-network under my plan? And can you tell me whether this service uses a copay or coinsurance, and whether my deductible needs to be met first?”
Pro Tip: When you open the SBC, use Ctrl+F and search “specialist” or “lab” to jump directly to the cost-sharing row for the service you need. It’s faster than reading the whole document.
When telehealth or direct-pay care removes the copay guessing game
For routine conditions, telehealth and direct-pay models can make your cost completely predictable before you even log in. No copay tiers, no deductible surprises, no separate lab billing.
| Factor | Insurance-based visit | Telehealth / direct-pay visit |
|---|---|---|
| Price before care | Estimated; depends on service type | Fixed, listed upfront |
| Deductible impact | Possible | None |
| Network verification needed | Yes | No |
| Suitable for complex diagnostics | Yes | Limited |
| Billing surprises | Common | Rare |
The tradeoff is real: telehealth and direct-pay work well for sinus infections, rashes, prescription refills, and quick follow-ups, but they’re not a substitute for inpatient care, complex imaging, or surgical consultations. Direct-pay models avoid copay and deductible complexity by replacing variable cost-sharing with a single transparent price. For patients who want to understand when going without traditional insurance makes financial sense, the real advantages of direct-pay care are worth reading before your next open enrollment decision.
Key Takeaways
Most copay surprises trace back to one root cause: assuming a flat fee covers more than the plan actually promises.
| Point | Details |
|---|---|
| Copays don’t reduce your deductible | They count toward your MOOP, but most plans keep copays and deductibles in separate buckets. |
| Service type determines cost-sharing | Labs, imaging, and inpatient stays often use coinsurance, not a copay, even during a copay visit. |
| HDHPs change the rules | Non-preventive services typically require you to pay the negotiated rate until the deductible is met. |
| The SBC is your best tool | Search it by service type before scheduling to find the exact copay, coinsurance, or deductible rule. |
| Chameleonhc offers fixed-price telehealth | For routine conditions, Chameleonhc’s transparent pricing removes copay and deductible uncertainty entirely. |
The part of copay confusion nobody talks about
The biggest problem with health insurance copay myths isn’t that people are careless. It’s that the system is genuinely designed in a way that makes misunderstanding almost inevitable. A plan hands you a card with three numbers on it, and you’re expected to know that those numbers apply only to specific service tiers, only in-network, only for certain visit types, and only after a separate deductible rule that may or may not interact with those numbers at all.
What actually helps is treating the SBC as a living document rather than a one-time enrollment form. The patients who avoid surprise bills are the ones who check it before scheduling, not after receiving a confusing EOB. Copays are predictable when you know where to look. The rest of the cost-sharing system is not, and that’s the honest reason why so many people leave a routine appointment thinking they’re covered and then open a bill two weeks later that says otherwise.
Clear pricing, no copay math required
If you’re tired of calculating what a visit will actually cost before you can book it, Chameleonhc offers a straightforward alternative. With transparent, upfront pricing and no insurance required, you know your cost before you connect with a licensed provider.

Chameleonhc works especially well for the kinds of visits where copay confusion tends to strike hardest: routine primary care, prescription management, and common conditions like heartburn or respiratory symptoms that don’t need an ER but still need real medical attention. Same-day access, no waiting room, and a price you can see before you start.
Ready to skip the guesswork? Visit Chameleonhc to see current visit pricing and connect with a provider today.
Authoritative sources worth bookmarking
These are the best places to verify copay rules, compare plans, and understand your rights as a patient:
- Understanding copays | UnitedHealthcare
- Coinsurance vs Copays: What’s the Difference? | Investopedia
- What Is a Copay in Health Insurance? | MoneyGeek
- Summary of Benefits and Coverage | HealthCare.gov
- Do copays count toward your health insurance deductible? | Verywell Health
- Copay vs Deductible: What’s the Difference? | MetLife
- AMA Foundation
- Subsidy calculator | KFF
Suggested search phrases to find your plan documents quickly: “my plan SBC,” “[insurer name] member portal SBC,” or “[employer name] benefits summary PDF.”
This article provides general information about U.S. health insurance cost-sharing. It is not professional insurance or financial advice. Confirm your plan’s specific rules with your insurer, your employer’s HR department, or a licensed insurance professional.