

The single most effective moves you can make right now are: run a utilization audit, tighten pharmacy controls (especially GLP-1 and specialty drugs), expand telehealth and virtual-first primary care access, and optimize your plan design and funding model. 54% of employers now identify cost as the single most important factor in benefits decision-making, so you are not alone in feeling the pressure to act.
Immediate action checklist (start this week):
- Pull your claims data and request a full utilization report from your carrier
- Ask your PBM for a specialty drug spend breakdown by therapeutic class
- Confirm telehealth is actively promoted and accessible to all eligible employees
- Identify whether a high-deductible health plan (HDHP) with an HSA option is available or feasible
30–90 day quick-action timeline:
- This week: Request carrier and PBM data; schedule a benefits audit kickoff with your broker
- This month: Review pharmacy formulary controls; communicate telehealth access to employees
- Next quarter: Evaluate plan design changes (HDHP, tiered networks, funding model) and set benchmark targets
These benefit package cost reduction tips are sequenced by speed-to-savings and employee experience risk. The sections below give you the detail to execute each one.
Key Takeaways
The most effective approach to reducing benefit package costs combines a data-driven audit, targeted pharmacy controls, and virtual-first care access — sequenced to protect employee experience while delivering measurable savings within 3–18 months.
| Point | Details |
|---|---|
| Start with the audit | Pull carrier and PBM claims data first — every other tactic depends on knowing your actual cost drivers. |
| Pharmacy controls deliver fast savings | Formulary optimization, prior authorization, and specialty channel enforcement typically yield near-term results within 1–3 months. |
| Telehealth reduces utilization cost | A well-promoted virtual-first benefit can divert 15–25% of avoidable ER and urgent care visits over 9–12 months. |
| Sequence by employee risk | Begin with low-risk tactics (audit, telehealth, pharmacy); reserve HDHP transitions and network changes for after you have utilization data to support the case. |
| Chameleonhc fits the virtual-first model | Chameleonhc’s employer plans offer same-day telehealth access with transparent subscription pricing, reducing both utilization costs and admin friction. |
Table of Contents
- How do you run a benefits audit and benchmark against peers?
- What plan-design and funding changes actually lower employer spend?
- How do you control pharmacy costs, especially specialty drugs?
- How does telehealth reduce your overall benefits costs?
- How do voluntary benefits shift costs without cutting package value?
- What wellness and population health programs actually pay off?
- How do you negotiate with carriers, PBMs, and benefit vendors?
- What is the right sequence and timeline for cutting benefits costs?
- Why aggressive cost-shifting is riskier than it looks
- Chameleonhc makes telehealth-first employer plans straightforward
- Sources
How do you run a benefits audit and benchmark against peers?
A benefits audit is where every meaningful cost-reduction effort starts. Before you can reduce benefit package expenses, you need to know exactly where the money is going.
Step-by-step audit checklist:
- Request a full ER claims file from your carrier (inpatient, outpatient, ER by diagnosis code)
- Pull Rx spend by NDC (National Drug Code) and therapeutic class from your PBM
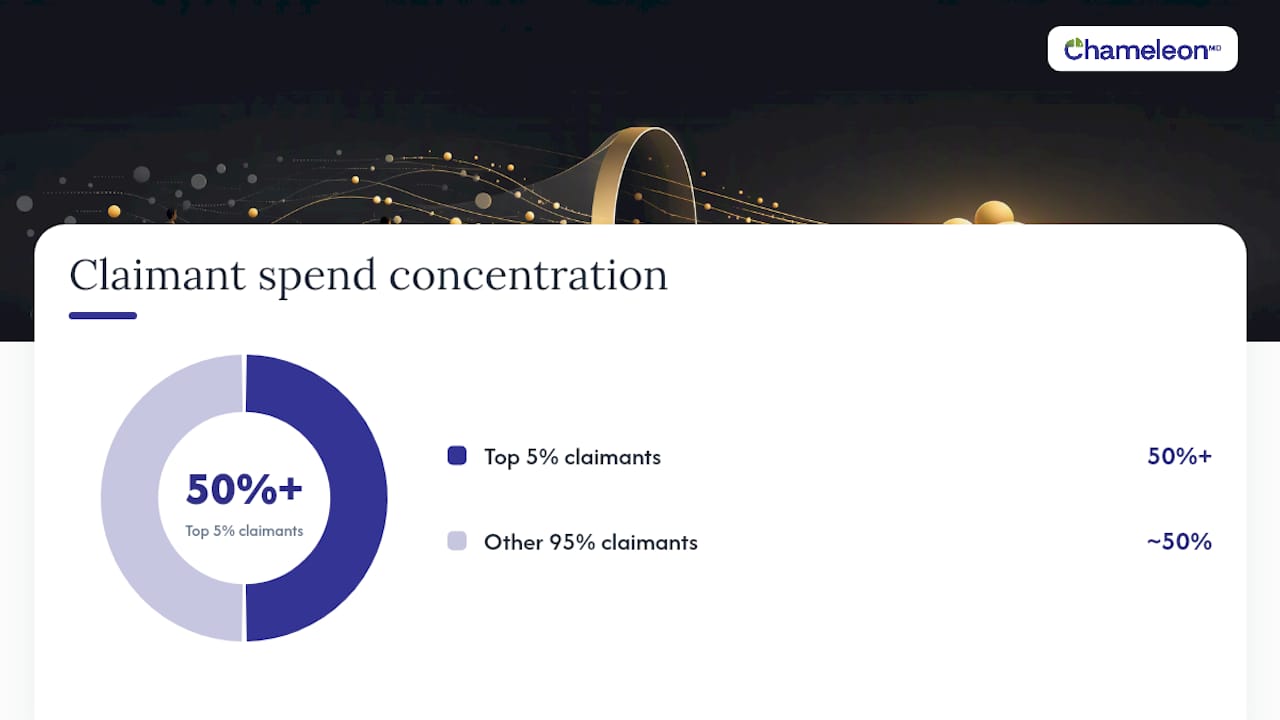
- Identify high-cost claimants (typically the top 5% driving 50%+ of spend)
- Review stop-loss attachment points and any lasered claimants
- Audit vendor and admin fees line by line (TPA fees, wellness platform costs, EAP, voluntary benefit admin)
- Check voluntary benefit uptake rates — low uptake signals a communication or enrollment problem
Data to request from carriers and PBMs:
- Medical claims file with diagnosis and procedure codes
- Pharmacy claims by NDC, drug name, and therapeutic class
- Utilization rates: ER visits, specialist referrals, urgent care, and virtual care
- Admin fee schedules and any pass-through vs. retained rebate disclosures
Once you have the data, compare it against external benchmarks. KFF employer-sponsored health insurance data is a reliable starting point for per-employee-per-year (PEPY) medical and pharmacy spend comparisons.
| Benchmark Metric | What to Measure | Why It Matters |
|---|---|---|
| PEPY medical spend | Total medical claims ÷ covered employees | Reveals overall cost position vs. industry peers |
| Specialty drug % of total Rx spend | Specialty claims ÷ total pharmacy spend | Specialty drugs often drive a significant portion of pharmacy costs |
| Virtual care utilization rate | Telehealth visits ÷ total medical visits | Low rates signal underpromotion or access barriers |
| ER visit rate per employees | ER claims ÷ covered lives | High rates indicate avoidable utilization |
| Wellness program participation | Enrolled ÷ eligible employees | Predicts long-term chronic-condition cost trajectory |
Brown & Brown’s 2026 employer survey confirms that audits, pharmacy RFPs, and stop-loss reviews are among the most common cost-containment tactics employers are using right now — which means your peers are already doing this work.
What plan-design and funding changes actually lower employer spend?
Plan design is where you have the most direct control over cost. The key is choosing levers that reduce spend without creating so much financial friction that employees avoid necessary care.
Core plan-design levers:
- HDHP + HSA: Shifts first-dollar cost to employees while preserving tax advantages. IRS Publication P969 governs HSA contribution limits and eligibility rules — review it before any plan-design change. HDHPs tend to reduce overall utilization, though they carry a risk of employees deferring preventive care.
- HRA (Health Reimbursement Arrangement): Employer-funded, employer-controlled. An Individual Coverage HRA (ICHRA) lets you reimburse employees for individual market premiums, which can reduce group plan administrative complexity.
- Tiered networks: Steer employees toward high-value, lower-cost providers by assigning lower cost-sharing to preferred facilities. Works best when paired with clear employee communication.
- Dependent eligibility audits: Removing ineligible dependents from coverage is one of the fastest ways to reduce benefit package expenses with no impact on active employees.
Funding model options:
- Fully insured: Predictable premiums, but you pay for the carrier’s risk margin. Best for small employers (under 50–100 lives) with limited risk tolerance.
- Self-funded: You pay claims directly; stop-loss insurance caps catastrophic exposure. Typically saves 10–15% on administrative costs versus fully insured, though cash-flow volatility is real.
- Level-funded: A hybrid model with fixed monthly payments and a claims reconciliation at year-end. Lower risk than full self-funding and often accessible to employers with 25+ employees.
Employers are using a mix of HDHPs, wellness initiatives, and self-insurance rather than relying on any single tactic — a sign that no one lever is sufficient on its own. See the affordable healthcare plan comparison guide for a side-by-side look at HDHP, PPO, and alternative models.
Pro Tip: Before moving to self-funding, model at least three years of claims history. A single catastrophic claimant year can distort the picture. Ask your stop-loss carrier for specific and aggregate attachment point options before finalizing the structure.
How do you control pharmacy costs, especially specialty drugs?
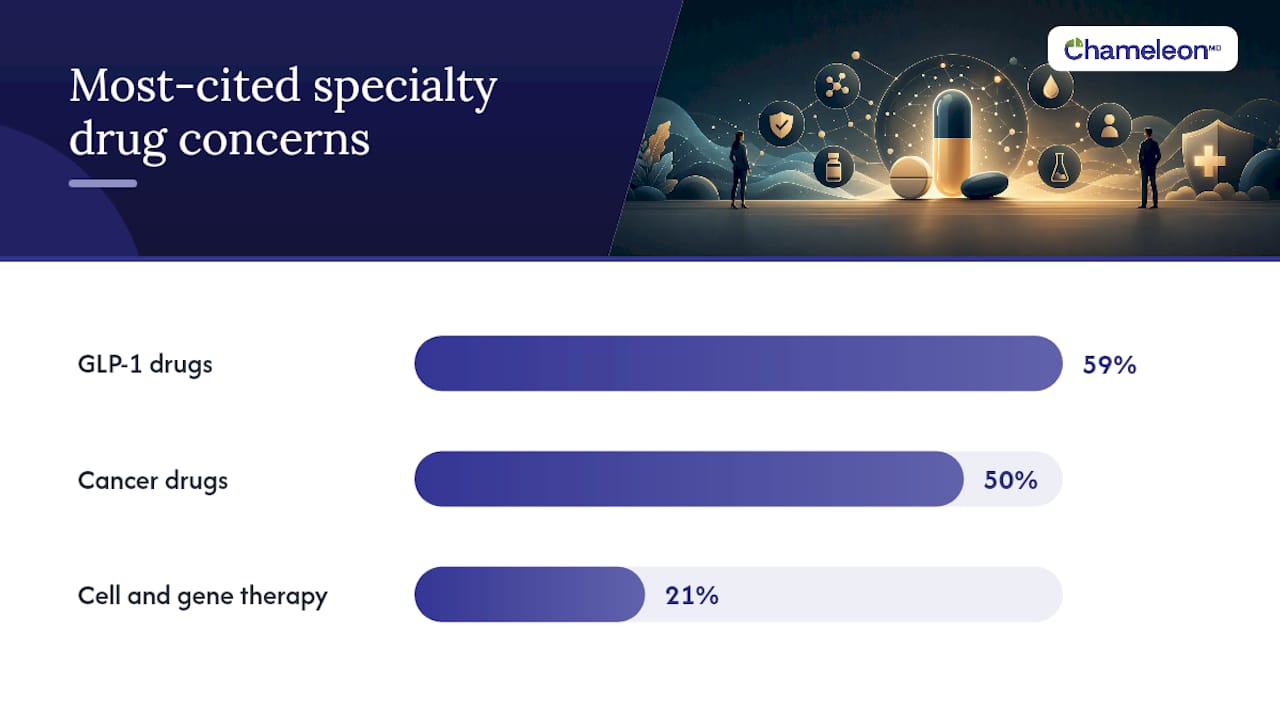
Pharmacy is now the fastest-growing cost driver in most employer health plans. Employers expect medical plan costs to keep rising, with GLP-1 drugs (cited by 59% of employers), cancer drugs (50%), and cell and gene therapy (21%) leading specialty drug cost concerns. Acting here delivers some of the largest near-term savings available.
High-return pharmacy cost controls:
- Formulary optimization: Remove or restrict brand drugs where generics or biosimilars are clinically equivalent
- Prior authorization (PA): Require PA for high-cost specialty drugs before dispensing
- Step therapy: Mandate trials of lower-cost alternatives before approving specialty medications
- Site-of-care management: Redirect specialty drug infusions from hospital outpatient settings (highest cost) to physician offices or home infusion (significantly lower cost)
- Specialty channel enforcement: Require specialty drugs to be dispensed through a designated specialty pharmacy rather than retail
- Mandatory lifestyle/behavior program enrollment: For GLP-1 coverage, top-performing employers require enrollment in behavior and lifestyle management programs as a condition of coverage — this reduces inappropriate utilization and improves clinical outcomes
Evaluating your PBM:
Many employers rank pharmacy management among their top cost-control approaches for 2026, and a growing number are moving to transparent or pass-through PBM models. Ask your current PBM:
- Are rebates passed through 100%, or does the PBM retain a portion?
- What is the spread between ingredient cost and what you are billed?
- Do you have audit rights on claims data?
If the answers are vague, it may be time to issue a pharmacy RFP. Specialty drug resources from partners like Roen can provide additional context on specialty distribution options.
How does telehealth reduce your overall benefits costs?
Virtual-first primary care is one of the most practical ways to lower healthcare benefit costs without reducing coverage. When employees can connect with a licensed provider online for common conditions — sinus infections, rashes, sprains, or urgent concerns — they skip the ER or urgent care clinic visit entirely. That redirection matters: ER visits cost employers several times more than a telehealth encounter for the same presenting complaint.
Employers are increasingly adopting advanced primary care and navigation models to steer employees toward higher-value care, and virtual-first platforms are a core part of that shift. The employer guide to fast workforce care covers urgent-care diversion in detail.
Implementation checklist:
- Define which conditions and visit types are covered under the telehealth benefit
- Confirm integration with your EAP and primary care network
- Set up eligibility and enrollment so employees can access care on day one
- Actively promote the benefit — utilization stays low when employees do not know it exists
- Measure virtual care utilization quarterly and track ER diversion rates
| Implementation Phase | Timeline | Expected First Savings |
|---|---|---|
| Vendor selection and contract | Months 1–2 | None yet |
| Enrollment and launch | Month 3 | Minimal |
| Active promotion and utilization ramp | Months 4–6 | ER diversion begins |
| Measurable cost impact | Months 9–12 | Moderate, trackable |
| Full ROI visibility | Month 18+ | Sustained reduction |
Conservative impact estimates suggest a well-promoted telehealth benefit can divert a notable share of avoidable ER and urgent care visits. More aggressive virtual-first models — where telehealth is the default first point of contact — can push that figure higher over time. The 2026 HR guide to telemedicine walks through measurement and integration in detail.
How do voluntary benefits shift costs without cutting package value?
Voluntary and supplemental benefits let you preserve a competitive total rewards package while moving a portion of cost off the employer’s book. The key is choosing benefits employees actually want and making enrollment frictionless.
Effective voluntary benefit options:
- Supplemental medical (hospital indemnity, accident insurance) — fills gaps in HDHPs and reduces employee financial stress
- Dental and vision buy-ups — employees pay for enhanced tiers; employer maintains base coverage
- Critical illness insurance — employee-paid, high perceived value, especially for populations with chronic-condition risk
- Short-term disability buy-ups — employees can purchase additional income protection beyond the employer-sponsored base
- Employee-paid wellness programs (fitness reimbursement, mental health apps) — low cost, high satisfaction
Implementation tips:
- Bundle voluntary benefits with your primary carrier where possible to reduce administrative complexity
- Set up payroll deduction at open enrollment — post-tax or pre-tax depending on the benefit type
- Use targeted communication by employee segment (age, family status, income band) to drive uptake
- Keep the voluntary benefit menu to five or fewer options; too many choices suppress enrollment
Common pitfalls to avoid:
Low uptake is the most common failure mode, and it almost always traces back to poor communication rather than employee disinterest. Vendor proliferation is the second: adding five separate voluntary benefit vendors creates five separate admin relationships, five data feeds, and five renewal conversations. Consolidate where you can.
What wellness and population health programs actually pay off?
Wellness programs have a mixed reputation, but targeted population-health investments — particularly chronic-condition management and care navigation — do generate measurable returns over a 2–3 year horizon.
Program types with evidence of ROI:
- Advanced primary care / virtual-first primary care: Replaces fragmented urgent care utilization and reduces specialist referrals over time
- Chronic care management: Structured support for employees managing diabetes, hypertension, or heart disease reduces hospitalizations and ER visits. Chronic disease management programs that include regular monitoring and coaching show consistent reductions in acute care utilization
- Care navigation and coaching: Guides employees to the right level of care at the right time, reducing unnecessary specialist visits and duplicate testing
- Condition-specific pathways: Musculoskeletal, maternity, and behavioral health pathways each address high-cost, high-frequency claim categories
Metrics to track:
- Readmission rates and ER visit frequency for enrolled chronic-condition members
- Engagement rates (enrolled vs. eligible, active vs. passive participants)
- Clinical outcomes: HbA1c control, blood pressure readings, BMI trends
- Total cost of care for program participants vs. a matched non-participant cohort
Pro Tip: Consolidate point solutions into a single navigation or virtual-primary-care platform. Employers running six separate wellness vendors often find that data sits in six silos, making it impossible to calculate true ROI. One integrated platform gives you a single view of utilization, outcomes, and cost — and reduces the vendor management burden significantly. Segal’s 2026 health-plan cost trend insights support this consolidation approach.
How do you negotiate with carriers, PBMs, and benefit vendors?
Negotiation is where employers with good data consistently outperform those without it. Your claims history, benchmark comparisons, and utilization trends are your leverage — use them.
Negotiation levers to use:
- Pricing guarantees: lock in admin fee caps for 2–3 years
- Pass-through transparency: require 100% rebate pass-through from your PBM
- Shared savings clauses: negotiate a share of any savings generated by formulary or network changes
- Outcome-based KPIs: tie a portion of vendor fees to measurable performance (ER diversion rates, engagement rates, clinical outcomes)
Contract clauses to request:
- Audit rights on all claims data, including pharmacy
- Data access provisions — you own your claims data, not the vendor
- Performance credits if utilization or quality targets are missed
- Termination-for-convenience clauses with reasonable notice periods
- Transparent fee schedules with no hidden administrative charges
When to run an RFP or hire a consultant:
- Run a medical or pharmacy RFP every 3–5 years, or sooner if costs are rising faster than benchmarks
- Hire an independent benefits consultant (not a commission-based broker) when you lack internal benchmarking capability or when a major plan redesign is under consideration
- A good consultant should deliver: benchmarking analysis, RFP management, vendor consolidation recommendations, and a written summary of findings with cost-impact estimates
Employers report audits, pharmacy RFPs, and stop-loss reviews among the most common cost-containment tactics in 2026. If you have not run a pharmacy RFP in the last three years, that is likely your fastest path to near-term savings. See also the employee healthcare streamlining guide for operational tips on reducing admin costs.
What is the right sequence and timeline for cutting benefits costs?
Not every cost-reduction tactic carries the same employee experience risk. The prioritization framework below helps you sequence actions so you protect retention while unlocking savings.
Prioritization matrix: impact vs. employee risk
Decision checklist for each major tactic:
- Who signs off? (HR lead, CFO, CEO for major plan changes)
- What is the employee communication plan and timeline?
- How will you measure success? (specific metric, baseline, target)
- What is the rollback plan if employee satisfaction drops sharply?
Pro Tip: Start with the lowest-risk, highest-data tactics first — audit, telehealth promotion, and pharmacy controls. These generate savings without touching the plan design employees see on their benefits summary. Reserve HDHP transitions and network changes for after you have 12 months of telehealth utilization data to show employees the value they are getting.
Aon’s employer strategies research confirms that adjusting employee cost-sharing and pharmacy management are the top approaches employers are prioritizing — but the sequencing matters as much as the tactics themselves.
Why aggressive cost-shifting is riskier than it looks
The temptation when facing a 10–15% benefits cost increase is to shift as much as possible to employees as quickly as possible. It feels like the cleanest lever. But the data tells a more complicated story.
When employees feel the financial weight of a plan change — a higher deductible, a narrower network, a new specialty drug restriction — the first thing many do is defer care. Deferred care for chronic conditions tends to resurface as a more expensive acute event 12–18 months later. You have not reduced cost; you have delayed it and made it worse.
The more durable approach is what Mercer and others call value-based steering: using analytics to identify high-cost drivers and then directing employees toward higher-value providers, virtual-first care, and Centers of Excellence — rather than simply raising their out-of-pocket exposure. The difference is that value-steering gives employees a better option, not just a more expensive one.
There is also a retention dimension that HR leaders sometimes underweight. Benefits are consistently ranked among the top three factors in job acceptance and retention decisions. A plan redesign that saves $400 per employee per year but triggers even a modest uptick in voluntary turnover can easily cost more in recruiting and onboarding than it saved. The metric to watch is voluntary turnover rate in the 6–12 months following any major plan change — not just claims cost.
The most effective benefit cost management strategies tend to share one characteristic: they give employees a genuinely better experience at a lower cost, rather than asking them to accept less. Telehealth is the clearest example. Employees get faster, more convenient care; employers pay less per encounter. That alignment is what makes it sustainable.
Chameleonhc makes telehealth-first employer plans straightforward
Cutting benefits costs while keeping your team well-supported is exactly the balance Chameleonhc is built for. Chameleonhc’s telehealth-first employer plans give your employees same-day access to licensed providers for urgent care, primary care, and common conditions — no waiting rooms, no insurance friction, and transparent pricing your finance team can actually plan around.

The model maps directly to the tactics in this article: virtual-first primary care reduces ER and urgent care utilization, membership-based pricing replaces unpredictable per-claim costs, and the subscription structure keeps admin overhead low. Employees can connect from their phone or computer to address conditions ranging from vomiting to chronic condition check-ins, all within the same platform. For employers looking to add a cost-effective, high-value benefit that employees will actually use, explore Chameleonhc’s employer plans to see pricing and coverage options.
Sources
These are the primary sources HR leaders and benefits teams should reference when building a business case or validating plan-design decisions.
- Employer strategies for rising healthcare costs — Aon
- 2026 Lockton National Benefits Survey — Executive Summary
- Employer Health Care Strategy Survey — Business Group on Health
- How employers are managing healthcare costs in 2026 — Pearl Meyer
- Brown & Brown — 2026 Employer Health and Benefits Strategy Survey
- IRS Publication P969
- KFF — Cost of health insurance
This article is general information, not a substitute for advice from a qualified financial advisor. Consult a qualified financial professional about your own circumstances before acting on anything here.